Liminality – holding space for spirituality

Liminal spaces feel uncomfortable because they are uncertain, unfinished, and difficult to control. Yet they are also places of growth, transformation, and discovery.

One of the most helpful ways of understanding healthcare chaplaincy is through the concept of liminality.

The word comes from the Latin limen, meaning “threshold”. It describes those in-between places where people have left what they once were but have not yet become what they will be. We encounter liminality during times of transition, uncertainty, loss, change, and possibility.

Hospitals are full of these threshold spaces. Illness, recovery, dying, grief, birth, trauma, hope, and uncertainty all create moments where the familiar gives way to the unknown.

Chaplains inhabit multiple liminal zones.
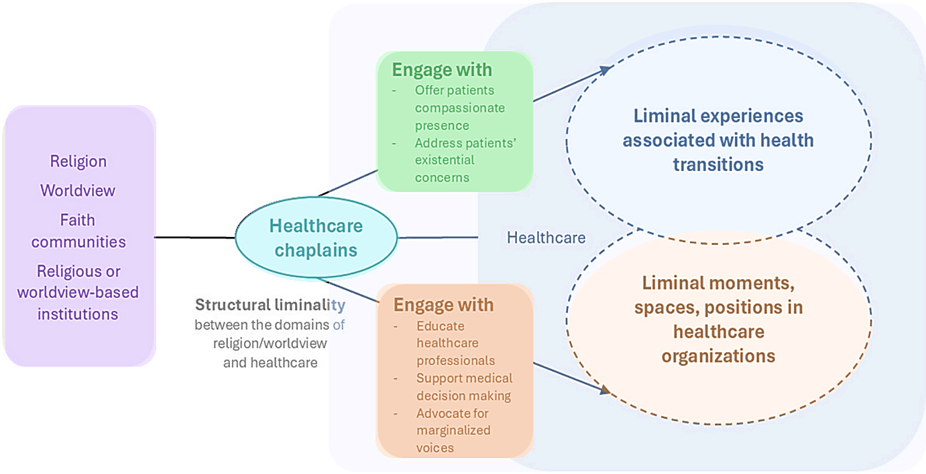
Fig. 1  The liminality model of healthcare chaplaincy.

The liminality of chaplaincy itself

Chaplaincy itself is a threshold vocation. As we work alongside healthcare teams, we also remain anchored in broader spiritual, religious, philosophical, and cultural traditions. Standing between worlds, translating, connecting, and creating space for conversation.

Clinicians primarily focus on diagnosis, treatment plans, and measurable outcomes, while chaplains attend to a different set of questions: those of meaning, personal formation, suffering, hope, purpose, belonging, and transcendence.

This can be an ambiguous space to inhabit, neither entirely inside nor outside healthcare. Yet this structural liminality is one of chaplaincy’s greatest strengths.

Because chaplains inhabit a threshold space, very often they become interpreters between competing worlds, helping patients and families navigate the complex culture of healthcare. They also help healthcare teams by communicating spiritual, existential, and relational concerns that can be easily missed.

In this way, chaplains provide a link by holding multiple perspectives at one time, facilitating conversations as deeper questions rise to the surface.

The liminality of the people we support

Chaplains meet people during significant transitions in their lives.

These transitions include unexpected diagnoses or events, the birth of a premature baby, progressive illness, the loss of independence, or the death of a loved one. Each disrupts a person’s assumptions about themselves, life, and the world around them.

Such moments suspend people between past and future. Vertigo and disorientation can set in; old certainties no longer hold, and nothing new has yet to emerge.

Liminality is rarely comfortable; it’s felt as a dark night of the soul in all its vulnerability, ambiguity, grief, and waiting, with unanswerable questions – a crucible or even a chrysalis.

While a chrysalis can appear still and fragile from the outside, it veils the deep transformation taking place within. During such times, deeper understandings, renewed relationships, unexpected strengths, and new awareness may emerge from experiences that felt only painful or uncertain.

A chaplain does not rush people through these spaces, and there are no easy answers. Through an active non-action, they hold space for others’ pain and uncertainty.

By offering attentive listening, compassionate presence, and space for reflection, chaplains help people ponder questions such as:

  • What matters most now?
  • How do I live with this loss?
  • What gives me hope?
  • How do I make sense of what is happening?
  • Who am I becoming through this experience?

Threads of meaning can emerge even as one lives through crisis or even chaos.

The liminality of the systems we work within

Liminality is not limited to the personal; it can be communal or organisational.

A hospital constantly juggles competing priorities: efficiency and compassion, policies and personhood, technology and humanity, evidence and meaning. They continually adapt to new challenges, changing expectations, and emerging realities that raise existential questions about spirituality, values, ethics, culture, and human flourishing, all while balancing competing demands.

Chaplains move between patients, families, clinical teams, community groups, executives, and healthcare systems, occupying a unique vantage point, noticing tensions and synergies between disparate departments or disciplines.

In this way, chaplains can meaningfully contribute to staff support, ethics consultation, reflective practice programs, memorial services, multidisciplinary discussions, and organisational conversations about wellbeing and culture, helping create organisational spaces where reflection and compassion remain part of healthcare’s ongoing conversation.

A practice of liminality

The language of liminality offers a helpful interpretive grid to evaluate chaplaincy.

Chaplaincy is better defined as a way of being rather than a set of tasks. It is a way of attending to people and accompanying people through their liminal zones. Noticing not only what is happening to them but also who they are becoming through it.

Liminal spaces are uncomfortable because they are uncertain and unfinished. Yet, paradoxically, they can also be places that foster growth, creativity, wisdom, and transformation.

In a fast-paced world eager for quick answers and clear resolutions, chaplains offer something different: a steady presence at the threshold, helping people, communities, and organisations find meaning and hope amid change.

Healthcare chaplains inhabit liminal spaces, accompany people through their own transitions, and help healthcare organisations remain attentive to questions of meaning and human flourishing.

A distinctive contribution of chaplaincy is its ability to remain in these liminal spaces, supporting others as they navigate their liminal zones with wisdom, compassion, and hope.

Based on insights from “A Foundation for Today’s Healthcare Chaplaincy in Western Societies: The Liminality Model” by Schuhmann, Varner-Perez, Lasair, Bradford, Peng-Keller, Nuzum, and Tuffnell.

Supervised Group Reflective Practice Still Matters—Beyond the Drift (Part 2)

Explore why supervised group reflective practice remains essential for chaplaincy formation and how education providers can sustain it in modern training. Review practical strategies and pathways to integrate reflective practice into contemporary programs.

Introduction

In Part 1, we explored the roots of supervised group reflective practice and why it remains essential for the formation of chaplains. We identified a growing tension: as academic programs expand, the embodied, communal learning that shapes competent spiritual care is slipping to the margins.

Reflective practice is costly, complex, and time-intensive. It doesn’t fit neatly into funding models or timetables. Yet without it, chaplaincy risks becoming theoretical—detached from the lived realities of suffering and hope. Formation happens in the crucible of experience and reflection—not in isolation, but in community. The question is: how do we design training that honours this truth, supports chaplains and those they care for, and meets students’ practical needs for sustained, structured, supervised reflective practice alongside ministry and workplace practicums?

Why Reflective Practice Matters

Clinical pastoral training for chaplains, pioneered by Richard Cabot and Anton Boisen, set a standard that remains relevant today. For decades, there has been broad agreement on a minimum standard for chaplaincy practicum in public institutions: a 400-hour unit of Clinical Pastoral Education (CPE) or an equivalent training program. The challenge lies in how “equivalency” is understood.


A typical 400-hour CPE unit in Australia weaves together four core components. First, Supervised Group Reflection occupies around 90 hours, usually delivered across 18 days at five hours per day, with about three-quarters of that time devoted to presenting pastoral encounters and engaging in reflective discussion. Second, students receive 10 hours of individual professional pastoral supervision, ensuring personal accountability and growth. Third, the clinical placement spans 160 hours, of which approximately 100 hours involve direct patient or client-facing care. Finally, study and assignments account for 140 hours, including the preparation of nine detailed pastoral encounter reports. These elements run concurrently, creating an integrated learning experience where theory and practice inform each other.

The critical feature of this model is that the work experience component is accompanied by sustained reflection in community—what we call Supervised Group Reflective Practice (SGRP). This is not an optional extra; it is the heart of formation.

Two Pathways Forward

To meet chaplaincy guidelines requiring a 400-hour unit of CPE or equivalent, education providers can consider two approaches. The first is to partner with an accredited CPE Centre and create a training pipeline for students. This preserves the traditional model and its proven strengths.

The second approach is to embed supervised practice within a course by designing a genuine 400-hour experiential component. This involves developing an equivalent tailored SGRP program in collaboration with a professional supervisor trained in a group supervision model—such as Value-Based Reflective Practices© developed in Scotland by chaplains. It is vital that the supervisor has experience providing professional-level chaplaincy or spiritual care. This ensures that the reflective process is grounded in real-world expertise.

Why SGRP Matters

The benefits of SGRP extend far beyond individual reflection. Trainees not only explore their own practice but also engage with 30 to 40 pastoral encounters from colleagues working in diverse settings such as mental health, aged care, defence, hospitals, and palliative care. This shared learning enriches everyone’s practice and fosters a deeper understanding of the spiritual challenges faced across different contexts. These challenges—grief, loss, suffering, trauma—are universal, reflecting what it means to be human in community.

Practical Implementation

SGRP can be delivered in various ways to suit different programs. Groups may meet in person, online, or in hybrid formats. Sessions can be scheduled weekly, fortnightly, in intensive blocks, or as retreats. An equivalent 400-hour unit can even be divided into two or three smaller units to fit semester or trimester structures. Education providers might also collaborate to create cross-institution groups, broadening the diversity of experience.

What Students Gain

Through this process, students learn to work competently with expressions of faith, religiosity, and spirituality. They internalise trauma-informed care, cross-cultural competency, and ethical frameworks, while also developing sector-specific skills such as dementia care, moral injury support, and mental health first aid. Reflective practice is structured through written reports that guide students to recall and explain encounters, apply models, explore spiritual issues, evaluate challenges, and generate insights for future practice. By the end of a 400-hour unit, students have reflected on their own eight to ten encounters and learned from thirty to forty of their peers’ experiences—a rich tapestry of learning that cannot be replicated through private reflection or theory alone.

A Closing Invitation

Cabot’s centenary is not nostalgia—it is an invitation. The spiritual needs of people have not changed. People still suffer and still search for words. Staff still carry burdens, and sustained, supervised group reflective practice is the most reliable way I know to become the kind of chaplain who can meet them.

There is this: practise, reflect, practise again—in community.