Liminality – holding space for spirituality

Liminal spaces feel uncomfortable because they are uncertain, unfinished, and difficult to control. Yet they are also places of growth, transformation, and discovery.

One of the most helpful ways of understanding healthcare chaplaincy is through the concept of liminality.

The word comes from the Latin limen, meaning “threshold”. It describes those in-between places where people have left what they once were but have not yet become what they will be. We encounter liminality during times of transition, uncertainty, loss, change, and possibility.

Hospitals are full of these threshold spaces. Illness, recovery, dying, grief, birth, trauma, hope, and uncertainty all create moments where the familiar gives way to the unknown.

Chaplains inhabit multiple liminal zones.
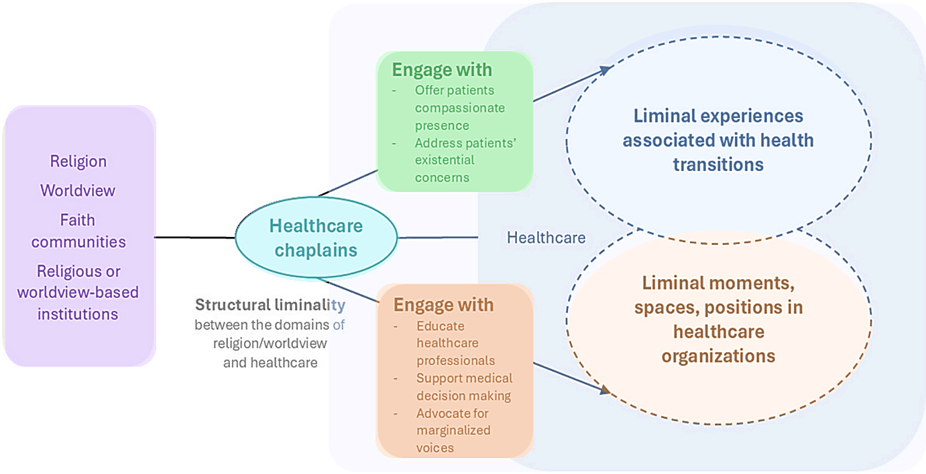
Fig. 1  The liminality model of healthcare chaplaincy.

The liminality of chaplaincy itself

Chaplaincy itself is a threshold vocation. As we work alongside healthcare teams, we also remain anchored in broader spiritual, religious, philosophical, and cultural traditions. Standing between worlds, translating, connecting, and creating space for conversation.

Clinicians primarily focus on diagnosis, treatment plans, and measurable outcomes, while chaplains attend to a different set of questions: those of meaning, personal formation, suffering, hope, purpose, belonging, and transcendence.

This can be an ambiguous space to inhabit, neither entirely inside nor outside healthcare. Yet this structural liminality is one of chaplaincy’s greatest strengths.

Because chaplains inhabit a threshold space, very often they become interpreters between competing worlds, helping patients and families navigate the complex culture of healthcare. They also help healthcare teams by communicating spiritual, existential, and relational concerns that can be easily missed.

In this way, chaplains provide a link by holding multiple perspectives at one time, facilitating conversations as deeper questions rise to the surface.

The liminality of the people we support

Chaplains meet people during significant transitions in their lives.

These transitions include unexpected diagnoses or events, the birth of a premature baby, progressive illness, the loss of independence, or the death of a loved one. Each disrupts a person’s assumptions about themselves, life, and the world around them.

Such moments suspend people between past and future. Vertigo and disorientation can set in; old certainties no longer hold, and nothing new has yet to emerge.

Liminality is rarely comfortable; it’s felt as a dark night of the soul in all its vulnerability, ambiguity, grief, and waiting, with unanswerable questions – a crucible or even a chrysalis.

While a chrysalis can appear still and fragile from the outside, it veils the deep transformation taking place within. During such times, deeper understandings, renewed relationships, unexpected strengths, and new awareness may emerge from experiences that felt only painful or uncertain.

A chaplain does not rush people through these spaces, and there are no easy answers. Through an active non-action, they hold space for others’ pain and uncertainty.

By offering attentive listening, compassionate presence, and space for reflection, chaplains help people ponder questions such as:

  • What matters most now?
  • How do I live with this loss?
  • What gives me hope?
  • How do I make sense of what is happening?
  • Who am I becoming through this experience?

Threads of meaning can emerge even as one lives through crisis or even chaos.

The liminality of the systems we work within

Liminality is not limited to the personal; it can be communal or organisational.

A hospital constantly juggles competing priorities: efficiency and compassion, policies and personhood, technology and humanity, evidence and meaning. They continually adapt to new challenges, changing expectations, and emerging realities that raise existential questions about spirituality, values, ethics, culture, and human flourishing, all while balancing competing demands.

Chaplains move between patients, families, clinical teams, community groups, executives, and healthcare systems, occupying a unique vantage point, noticing tensions and synergies between disparate departments or disciplines.

In this way, chaplains can meaningfully contribute to staff support, ethics consultation, reflective practice programs, memorial services, multidisciplinary discussions, and organisational conversations about wellbeing and culture, helping create organisational spaces where reflection and compassion remain part of healthcare’s ongoing conversation.

A practice of liminality

The language of liminality offers a helpful interpretive grid to evaluate chaplaincy.

Chaplaincy is better defined as a way of being rather than a set of tasks. It is a way of attending to people and accompanying people through their liminal zones. Noticing not only what is happening to them but also who they are becoming through it.

Liminal spaces are uncomfortable because they are uncertain and unfinished. Yet, paradoxically, they can also be places that foster growth, creativity, wisdom, and transformation.

In a fast-paced world eager for quick answers and clear resolutions, chaplains offer something different: a steady presence at the threshold, helping people, communities, and organisations find meaning and hope amid change.

Healthcare chaplains inhabit liminal spaces, accompany people through their own transitions, and help healthcare organisations remain attentive to questions of meaning and human flourishing.

A distinctive contribution of chaplaincy is its ability to remain in these liminal spaces, supporting others as they navigate their liminal zones with wisdom, compassion, and hope.

Based on insights from “A Foundation for Today’s Healthcare Chaplaincy in Western Societies: The Liminality Model” by Schuhmann, Varner-Perez, Lasair, Bradford, Peng-Keller, Nuzum, and Tuffnell.


Supervised Group Reflective Practice Still Matters—A Century After Cabot (Part 1)

Why does supervised group reflective practice still matter for chaplains a century after Richard Cabot’s call for clinical training? This post explores the roots of Clinical Pastoral Training and why embodied, reflective practice remains essential in today’s chaplaincy formation.

A century ago, Dr Richard Cabot issued a plea that still resonates: chaplains need more than theory—they need a clinical year. Not just books and lectures, but bedside learning—where life is raw and questions are real. Anton Boisen called patients “living human documents.” Those words remain luminous. They remind us that formation is not abstract; it happens in the presence of suffering, in the fragile spaces where meaning frays.

When I speak of Supervised Group Reflective Practice, I mean formation groups where pastoral encounters are brought for honest reflection and feedback—where peers ask the questions we’d rather avoid, and supervisors hold silence until insight comes. It’s the rhythm of noticing, wondering, and seeing. This practice shapes future encounters with new perception and awareness. And it’s not just for healthcare chaplains; it matters wherever professional spiritual care is offered—aged care, defence forces, mental health, prisons, and more.

Cabot and Boisen built their training model on the emerging discipline of social work, using case studies as the foundation. That approach gave rise to Clinical Pastoral Education (CPE), now the standard in many countries. The Association for Clinical Pastoral Education (ACPE) describes CPE as supervised encounters with people in crisis, grounded in feedback from peers and educators. The method is simple and profound: learn by doing, reflect in community, then return with practice reimagined.

Why does this matter? Because spiritual care is more than theory—it’s practice. Practice that works at the edge of suffering, where people search for words and those who care carry weight they cannot name. Reflection in community teaches us to stand there without flinching, to listen beneath the surface, and to remain in the tension without collapsing the space with quick fixes—to notice and wonder before seeing.

Spirituality is a dynamic, relational dimension of life. It shapes how people experience, express, and seek meaning, purpose, and transcendence. It includes how they connect—to themselves, to others, to nature, to the significant and the sacred. Good spiritual care improves quality of life, coping, and resilience. But competence is key. Chaplains need to move seamlessly between two principal modes of care: the reflective presence of compassionate listening and the reframing processes that help people find new meaning. They need to know which mode they’re in, when they shift, and why. Frameworks like the Living Wholeness CURE model (Dr John Warlow) or the Attuned Listener (Dr Jackie Perry, Columbia University) can scaffold these encounters. But these skills don’t come from books alone—they come from repeated practice, held and examined in the crucible of community reflection.

Here’s the challenge: chaplaincy training is increasingly embedded in university programs. That brings strengths—scholarship, research literacy, consistency. These matter. But as curricula grow, links to robust practical training become thinner. We risk forgetting John Dewey’s maxim: “We do not learn from experience…we learn from reflecting on experience.” A practicum that simply places a trainee in a workplace isn’t enough. True learning requires a disciplined program of supervised thought, reflection, and evaluation.

Practicums without supervised group reflection expose both trainee and care recipient to risk—care that lacks safety, care that may be ineffective, and trainees repeating the same mistakes. We see the need, yet feel the drift toward academia. Reflective practice groups are labour-intensive and costly, and they don’t fit neatly into funding models. In Australia, chaplaincy formation risks becoming over-theoretical. We need balance—embodied experience and communal wisdom alongside theology and pastoral theory. Integration, not substitution.

For years, a 400-hour unit of Clinical Pastoral Education or equivalent has been considered the minimum practicum for chaplaincy in hospitals, prisons, and defence forces. For Christian chaplaincy, this practicum sits alongside theological studies—neither replacing the other. Education providers have struggled to implement these sustained supervised practicums, often omitting structured reflective practice groups. The result? Programs that miss the heart of formation.


We stand at a crossroads: chaplaincy education risks becoming overly theoretical, while the need for embodied, reflective practice remains urgent. How do we reclaim what Cabot and Boisen knew—that formation happens in the crucible of experience and reflection? In Part Two, we’ll explore practical steps and models that can help us bridge this gap.

Caring for the Whole Person: Integrated Spiritual Care

The deepest kind of knowing is not about information—it’s about transformation. It’s about being with someone in their suffering, not above it. It’s about mutual presence, shared vulnerability, and the sacred dance of trust.

As spiritual carers, we often find ourselves standing at the threshold of mystery. A person’s suffering, their questions, their silence—all invite us into something deeper than diagnosis or doctrine. But how do we, as spiritual carers, respond wisely and compassionately without falling into a patchwork of disconnected theories?

This is where John Vervaeke’s 4P knowing might help.


Philosopher and cognitive scientist John Vervaeke offers a framework that helps us hold the complexity of human experience with integrity through the dimension of four kinds of knowing:  Propositional, Procedural, Perspectival, and Participatory. These categories explore the length, breadth and depth through the unfolding experience of time.

Being aware of these dimensions allows us to subtly tease apart the laminated layers of experience, which are much more than just academic categories—they help us attend to the whole person.


1. Propositional knowing: held in the head

This is the realm of facts, beliefs, and ideas—the “head” knowledge. It’s where theology and philosophy live, where doctrines and theories are debated. But propositional knowing has its limits. It is a distillation of lengthy deliberations stripped of their particularity—the map, not the terrain. Propositions orient us and set our direction, but they lack specificity. They rarely answer the individual cries of “Why did this happen to me?” or “Where is God in this?”

When someone is in crisis, their beliefs may no longer make sense. They may feel betrayed by the very truths they once held dear. This is the terrain of cognitive dissonance, where what we believe and what we experience no longer align.

In these moments, explanations, shallow solutions or fast resolutions fall short. We work with the “is,” not the “ought.” We honour the real, not the ideal. We are listening for the deeper questions beneath the surface, knowing that some truths can only be lived, not solved.


2. Procedural knowing: held in the body

Procedural knowing is embodied. It’s the knowledge of the body, of habits, of rituals, of the unspoken. It may take the form of absent-mindedly pouring a cup of tea, or the pattern of folded hands to receive communion, the rhythmic pounding of the pavement on a run or the instinctual understanding that accompanies bike riding. Or, it might take the form of intuition or the sensation of having hit the car’s brakes before you even saw the child running out between parked cars.

This type of understanding is particularly crucial in trauma-informed care. The body remembers what the mind cannot articulate. Emotions, sensations, and gestures often speak louder than words.

Here, spiritual care becomes accompaniment. We meet people in their rituals, their silence, and their tears. We use poetry, music, liturgy, and touch (when appropriate) to communicate love and safety. We recognise that even those who cannot articulate their faith may still live deeply spiritual lives.


3. Perspectival knowing: held in the story

Perspectival knowing is about context. It’s about how people see the world, how they interpret their experiences, and how their stories shape their identity.

This is where narrative becomes a powerful vehicle. By helping people see their stories in a different light, we invite them to see their lives through new lenses.

We draw on metaphors, parables, and even paradoxes to help people find meaning. We honour their “horizons of significance,” as philosopher Charles Taylor puts it, and gently expand them. We don’t impose our perspective—we help them discover their own.


4. Participatory knowing: held in the heart

Finally, participatory knowing is relational. It’s the “I-Thou” space described by Martin Buber, where we meet each other not as problems to be solved, but as sacred beings to be encountered.

This is the deepest kind of knowing. It’s not about information—it’s about transformation. It’s about being with someone in their suffering, not above it. It’s about mutual presence, shared vulnerability, and the sacred dance of trust.

In participatory knowing, we don’t just offer care—we become part of the care. We pray together, we cry together, we sit in silence together. We become companions on the journey, not just guides.


Why it matters

In spiritual care, no single kind of knowing is enough. Wisdom engages all dimensions of knowing. We need the clarity of the head, the habits and intuitions of the body, the insight of the story, and the intimacy of the heart.

This is especially true in spiritual care, where the boundaries between life and death, hope and despair, justice and injustice, and faith and doubt become porous. Here, the spiritual carer must be fluent in all four languages, able to move gently between them as the moment requires.


The content of the post is drawn from pages 16-18 of a journal article I wrote in 2022. The rough draft was created from the article with the help of an AI assistant, and then I refined it personally. The 4P infographic draws on summarised material from the article by Vervaeke and Ferraro.

Confusing a reflection with its reality

Spiritual and religious practices are not coping mechanisms although they may help a person cope.

Research into the relationship between religiosity, spirituality, and health is a growing field that has gained significant attention in academic literature. Many studies now show that people who describe themselves as religious and/or spiritual also demonstrate a positive association with attributes such as a sense of meaning and purpose, peacefulness, psychological well-being, and social connections.

However, concerns have been raised that some measures of religiosity and spirituality (R/S) may be contaminated with indicators of mental health in the research questions, leading to tautological associations. One way of envisioning this problem is to mistake a reflection for the reality it represents and then be surprised by the coincidence that the reflection and the reality resemble each other so closely.

Some confusion arises from the difference between practice and research. 1) Spiritual and religious care practices concerning the whole person include physical, mental, and social well-being. Care is provided through concern that connects through compassionate presence and conversation. In contrast to spiritual and religious care, 2) research into the specific functions and modalities of religiosity and spirituality (R/S) focuses on the unique contribution of religious and spiritual practices, perspectives, and attitudes informed by religious, wisdom, philosophical, or spiritual traditions.

This problem is explained in a recent article by Harold Koenig (Professor of Psychiatry and Behavioral Sciences at Duke University School of Medicine) and Lindsay Carey (Associate Professor (Adjunct) with the Palliative Care Unit, School of Psychology and Public Health, in the School of Health, Science and Engineering at La Trobe University).

Koenig and Carey note that some religiosity and spirituality research scales do not clearly distinguish between different R/S factors and their connections, effects, and causes on health outcomes, mainly mental health, meaning and purpose, connections with others, peace, and existential well-being. Their article discusses concerns about R/S measurement scales, identifies examples of contaminated measures, and recommends uncontaminated measures for future studies.

It is necessary to separate the extrinsic spiritual and religious care provided to a person by a spiritual carer from the intrinsic religiosity and spirituality held by the person themselves.

It is necessary to separate the extrinsic spiritual and religious care provided to a person by a spiritual carer from the intrinsic religiosity and spirituality held by the person themselves. Once separated, it is then possible to evaluate the extent to which a person is enlivened and sustained by religious and spiritual practices, perspectives, beliefs, rituals and communities. Such religiosity or spirituality is more than a community belief or set of doctrines; it is held personally and is present already, or emerging, becoming an integral part of their person, functioning more like a spiritual endoskeleton than an exoskeleton.

A key feature of spiritual and religious practices is that they are not coping mechanisms although they may help a person cope. Religious and spiritual outlooks provide insights and evolving perspectives that engage topics as wide-ranging as life and death, suffering and injustice, mortality and divinity, good and evil, the sublime and the beautiful, guilt and forgiveness, concreteness and fleetingness, certainty and mystery, or finitude and infinity. Transformations happen through processes of prayer, contemplation, meditation, a sense of the mysterious or miraculous, gift or grace, a leap of faith or a journey into the unknown, or a willingness to take the road less travelled.

A religious or spiritual outlook may not necessarily change a person’s material circumstances. Still, it may provide an alternative perspective on events, which in turn reframes issues of meaning and purpose. Examples of religious or spiritual perspectives can be seen in the writings of Holocaust survivor Viktor Frankl’s Man Search for Meaning, a translation of a book written in German, with the original title, Nevertheless, Say “Yes” to Life: A Psychologist Experiences the Concentration Camp. Paul Kalanithi, a young neurosurgeon dying of a brain tumour, pondered the question of what makes a life worth living and wrote When Breath Becomes Air. Or the books of Kate Bowler, a sufferer and survivor of stage IV cancer, Everything Happens for a Reason: And Other Lies I’ve Loved or No Cure for Being Human: (and Other Truths I Need to Hear).

Roger Gottlieb wrote that we often think of spirituality as soothing music, peaceful countryside settings, or compliant love, however, spiritual teachings are quite radical. Jesuit theologian Walter Burghardt once described contemplation as taking a “long, loving look at the real.” Religious and spiritual practitioners practice long, loving looks at the ‘real’ holding another in a loving gaze, not a passing glance, and together, they explore the reality, caught only in shimmering and fragmentary reflections.